
Buprenorphine Low-Dose Induction using a Cross-Tapering Strategy
If you need support or linkage to care after your emergency department, hospital, or clinic visit, call the CareConnect Warmline at 484-278-1679 to speak with a substance use navigator.
Background
Buprenorphine is a mu-opioid receptor partial agonist that is indicated for pain management and the treatment of opioid use disorder (OUD). Traditional induction for patients with OUD requires a patient to experience opioid withdrawal (measured via the COWS score) prior to buprenorphine initiation. This is necessary in order to prevent the experience of precipitated withdrawal due to the partial agonist effects in the setting of a full opioid agonist when using high doses of buprenorphine (mg doses). Micro-dosing of buprenorphine uses microgram (mcg) doses, allowing for the induction of buprenorphine without the need to first experience withdrawal or the risk of precipitated withdrawal given the very small doses. In the inpatient setting, this can be accomplished through several formulations of buprenorphine that can be given in micrograms — buccal films (Belbuca®), patches (Butrans®), and intravenous buprenorphine. In the outpatient setting, this can be accomplished through cutting of sublingual films into smaller pieces. Doses are increased over 3-7 days to achieve full maintenance dosing.
Intent
For use as an alternative to standard or higher-dose buprenorphine induction strategies
Intended Patient Population
- Patients requesting buprenorphine treatment for OUD who have a history of illicit opioid use (fentanyl, in most cases) – UDS confirmation not necessary
AND
Who wish to avoid the need for moderate-severe withdrawal symptoms prior to induction with higher doses of buprenorphine.
- For example:
- Patients wishing to transition from methadone to buprenorphine
- Patients with chronic, heavy use of IV or intranasal fentanyl
- Patients who have experienced prior precipitated withdrawal
- In hospitalized patients, those who are being maintained on a full opioid agonist for the treatment of pain or withdrawal. In outpatients, those who are continuing to use full agonist opioids through the induction process.
- For example:
- Patients admitted with acute pain and concomitant OUD, requiring full agonist therapy for analgesia but wishing to initiate buprenorphine
- Patients on chronic opioids for analgesia and diagnosed with OUD who would like to be transitioned to buprenorphine for MOUD
Cross Tapering and Low Dose Microinduction Protocol for Admitted Patients
Buprenorphine Cross-Tapering using a Low-dose (microdosing) Strategy
Background
Buprenorphine is a mu opioid receptor partial agonist that is indicated for pain management and the treatment of opioid use disorder (OUD). Traditional induction for patients with OUD requires a patient to experience opioid withdrawal (measured via COWS scores) prior to buprenorphine initiation. This is necessary because high doses of buprenorphine, a partial opioid agonist, may cause precipitated withdrawal when used in the setting of a full opioid agonist. Low dose induction (microdosing) of buprenorphine uses the buprenorphine buccal films (Belbuca®), which are dosed in micrograms, allowing buprenorphine initiation without requiring withdrawal with a minimal risk of precipitated withdrawal. Doses are increased over 3-4 days to achieve full maintenance dosing. Case reports and case series have generally demonstrated success with this approach in hospital settings using a variety of different dosing approaches.
Intent
For use as an alternative to traditional buprenorphine induction strategies.
Intended Patient Population
- Patients requesting buprenorphine treatment who have a history of illicit opioid use (e.g. fentaNYL) AND who wish to avoid the need for moderate withdrawal symptoms prior to induction with standard starting doses of buprenorphine. UDS confirmation is not necessary.
- For example, patients stabilized on full agonist and transitioning to buprenorphine:
- From methadone
- Who have experienced prior precipitated withdrawal
- Without significant withdrawal symptoms at initiation
OR
- For example, patients stabilized on full agonist and transitioning to buprenorphine:
- Patients on full opioid agonist for treatment of pain AND who wish to initiate buprenorphine.
- For example:
- Patients admitted with acute pain and comorbid OUD, requiring opioids for analgesia
- Patients on chronic opioids for analgesia
- For example:
- This approach may also be used in pregnant patients (SAMHSA 2018).
Procedure
1. Full Opioid Agonist
Prior to buprenorphine micro-dosing induction, establish scheduled regimen of oxyCODONE, HYDROmorphone, fentaNYL, morphine, or methadone that is effective for pain, withdrawal, and cravings per patient report.
- Recommended full opioid agonist regimens:
- Long acting options – Oxycodone ER 40mg PO TID or Methadone 40mg PO daily PLUS
- Short acting options – Oxycodone IR 20mg PO q4h or hydromorphone IR 8mg PO q4h
2. Clinical Opioid Withdrawal Scale (COWS) Monitoring
- COWS should be documented throughout the induction process to monitor for withdrawal at least every 12 hours (e.g. with every other buprenorphine administration) and as needed based on withdrawal (e.g. nausea/diarrhea, cravings).
- If COWS scores rise, encourage patients to continue low dose (microdose) induction pathway. Offer non-opioid adjuvants or higher doses of full-agonist opioids for withdrawal symptoms. If patients prefer not to continue, pause buprenorphine, continue full-agonist opioids, and consider psychiatry consult.
Discharge Considerations
- Ensure early discharge planning for follow-up with buprenorphine provider and for OUD care.
- Provide Narcan® – utilize MyPennPharmacy for discharge prescription if available.
Low Dose (microdosing) induction regimen using Belbuca® and Suboxone® (Buprenorphine/naloxone)
- On Day 1, while continuing full-agonist opioids, use buccal buprenorphine 300mcg or 150 mcg per the chart below.
- After Day 2 or 3, consolidate total daily dose into once daily dosing as Suboxone® (buprenorphine/naloxone) once on a stable dose post-titration and prior to discharge.
- If needing assistance at any point during this titration, please contact the Opioid Stewardship Pharmacist (HUP only). If unavailable, reach out to Psychiatry.
| Day | Buprenorphine |
|---|---|
| Day 1 | *Buprenorphine (Belbuca®) 300 mcg buccal q4h OR Buprenorphine 150 mcg q3h *May consider either dosing schedule based on patient’s risk or fear of precipitated withdrawal and to allow for patient choice. Consider nursing staff capabilities in choosing the frequency of administration. |
| Day 2 | Buprenorphine/naloxone 2 mg SL q6h |
| Day 3 | Buprenorphine/naloxone 4mg SL q6h (alternatively 8mg q12h if preferred) |
| Day 4 | Full dose Buprenorphine/naloxone 16-24mg daily (may be split up BID or TID) |
Full Opioid Agonist
- Full agonists should be continued during this induction and may be tapered starting on Day 2 of induction OR discontinued once patients reach 16-24mg of buprenorphine/naloxone daily. The approach should be agreed upon with the patient.
- Full agonist therapy may also be continued after you reach the goal buprenorphine dose for pain or continued symptoms of withdrawal. Work with the patient to develop a taper plan that is reasonable and to optimize non-opioids for symptom management while tapering full agonist opioids.
- For transitions from methadone: For buprenorphine induction in patients on methadone doses of >80 mg daily it is recommended to seek expert consultation. Give the final dose of methadone on Day 1 and follow buprenorphine 150 mcg dosing titration protocol above. On day 2, you may give an additional 30 mg of methadone orally daily for persistent withdrawal symptoms.
For patients not tolerating anything in the oral cavity: Can use IV buprenorphine 300 mcg q6h on day 1; 600 mcg IV q6h on day 2; and 1200 mcg (1 gram) IV q6h on day 3.
Approximate Buprenorphine Equivalencies:
1 mg sublingual buprenorphine ≈ 450 mcg buccal buprenorphine ≈ 250 mcg IV buprenorphine
A note on tapering: All tapering should be done with shared decision-making with the patient. Optimize nonopioids to increase chances of success. See additional considerations above.
Patients on Chronic Opioids
- On day 1 of buprenorphine low dose (microdose) induction, maintain full agonist therapy. Day 2, decrease full agonist by 30-50% and then 25% every 2-3 days thereafter or as indicated based on expected acute/chronic pain trajectory.
For example: Baseline regimen: OxyCODONE ER 40 mg PO q12h and oxyCODONE 10 mg PO q6h (total daily oxyCODONE = 120 mg = oral morphine equivalent (OME) 180 mg) → Decrease 50% to oxyCODONE ER 20 mg PO q12h x 2 days and oxyCODONE 5 mg PO q6h x 2 days; then oxyCODONE 10 mg ER PO q12h and oxyCODONE 10 mg PO q8h x 2 days; then discontinue oxyCODONE ER and decrease to oxyCODONE 10 mg PO q12h x 2 days, then stop all oxyCODONE.
Patients on Opioids for Acute Pain
- If patients are having refractory pain on full dose buprenorphine/naloxone (16 mg/d), consider lowering the buprenorphine/naloxone dose to 8 or 12 mg daily and giving in split q6-8h dosing (i.e. 4 mg SL q8h or q12h) until the need for full opioid agonist for acute pain management resolves, at which time the buprenorphine/naloxone dose should be increased back up to the 16 mg total daily dose.
- Provide PRN opioid analgesic. Provide rapid taper (over 3-5 days) as acute pain resolves.
For example: Baseline regimen: OxyCODONE 10 mg PO q4h → Decrease 30% (Day 1) oxyCODONE 10 mg PO q6h x 2 days; then oxyCODONE 10 mg PO q12h x 2 days; then oxyCODONE 5 mg PO q12h x 2 days, then stop if full agonist is no longer needed.
References
- Antoine D, Huhn AS, Strain EC, Turner G, Jardot J, et al. Method for successfully inducting individuals who use illicit fentanyl onto buprenorphine/naloxone. Am J Addict. 2020.
- Brar R, Fairbairn N, Sutherland C, Nolan S. Use of a novel prescribing approach for the treatment of opioid use disorder: Buprenorphine/naloxone microdosing – a case series. Drug Alcohol Rev 2020;39:588-594.
- Klaire S, Zivanovic R, Barbic SP, Sandhu R, Mathew N, Asar P. Rapid micro-induction of buprenorphine/naloxone for opioid use disorder in an inpatient setting: A case series. Am J Addict 2019;28:262-265.
- Rozylo J, Mitchell K, Nikoo M, Durante SE, Barbic SP, et al. Case report: Successful induction of buprenorphine/naloxone using microdosing schedule and assertive outreach. Addict Sci Clin Pract. 2020;15:2. https://doi.org/10.1186/s13722-020-0177-x
- Substance Abuse and Mental Health Services Administration. Clinical Guidance for Treating Pregnant and Parenting Women With Opioid Use Disorder and Their Infants. HHS Publication No. (SMA) 18-5054. Rockville, MD: Substance Abuse and Mental Health Services Administration, 2018.
- Weimer MB, Guerra M, Morrow G, Adams K. Hospital-based Buprenorphine Microdose Initiation. J Addict Med. 2020. doi:10.1097/ADM.0000000000000745
Updated by: Emily Casey; additional input from Ashish Thakrar, Jeanmarie Perrone, Maggie Lowenstein, Navid Roder
Reviewed by: PPMC, PAH, PMPC, CCH, HUP, Oct 2023
Self-Guided Cross Tapering and Low Dose (2mg) Microinduction Protocol for Outpatients / Patient Discharge
Suboxone (Buprenorphine-Naloxone) Self-guided Micro-Induction Protocol with Cross-Taper
If you need support or linkage to care after your emergency department visit, call the CareConnect Warmline at 484-278-1679 to speak with a substance use navigator.
How to take your medicine:
Do not eat, drink, or smoke for 15 minutes before and 15 minutes after taking your medicine. Let the tablet or strip fully melt in your mouth. Try not to swallow or talk as you will take in less medicine.
Low Dose Suboxone® Start (“Micro-Induction”) with Cross-Taper:
You will start with a small amount of Suboxone and increase gradually over several days. You do not have to be in withdrawal to start, and you may use other opioids to comfort while your Suboxone dose is going up. You should stop using other opioids on Day 7.
You can follow the directions below or you can increase your dose of Suboxone more quickly or slowly if needed.
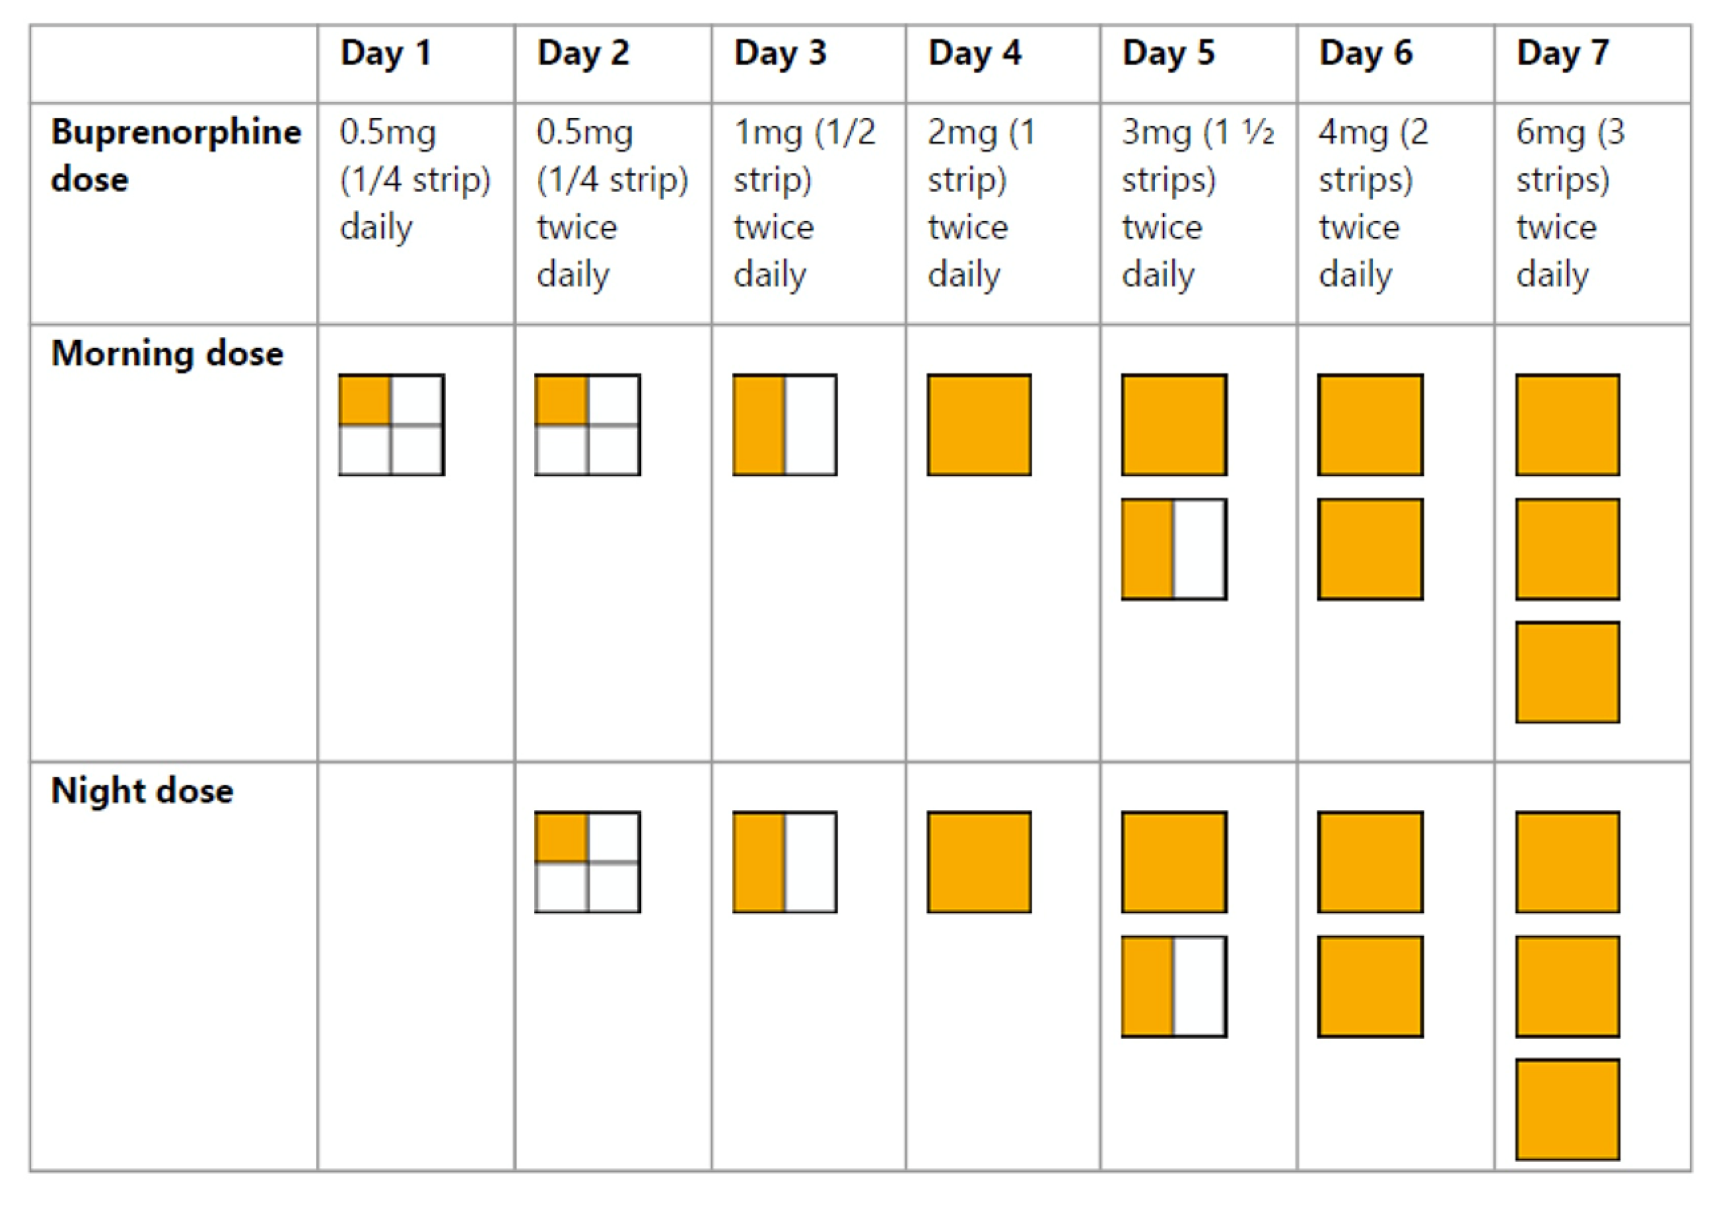
| Day | Morning dose | Night dose | Total daily dose |
|---|---|---|---|
| Day 1 | 0.5 mg (¼ strip) | None | 0.5 mg |
| Day 2 | 0.5 mg (¼ strip) | 0.5 mg (¼ strip) | 1 mg |
| Day 3 | 1 mg (½ strip) | 1 mg (½ strip) | 2 mg |
| Day 4 | 2 mg (1 strip) | 2 mg (1 strip) | 4 mg |
| Day 5 | 3 mg (1½ strips) | 3 mg (1½ strips) | 6 mg |
| Day 6 | 4 mg (2 strips) | 4 mg (2 strips) | 8 mg |
| Day 7 | 6 mg (3 strips) | 6 mg (3 strips) | 12 mg |
Day 1: How to take your first dose
- If you had your first dose in the emergency room: You are done for the day.
- If you are starting your first dose at home: Cut a 2 mg Suboxone strip into 4 pieces. Take one small piece (one quarter) of a strip. This is 0.5 mg.
Day 2
Continue using the first 2 mg Suboxone strip that you cut into 4 pieces from Day 1. Take one piece (0.5 mg) twice a day. Your total daily dose will be 1 mg.
Day 3
Cut a 2 mg Suboxone strip in 2 pieces. Take one half of a strip (1 mg) twice a day. Your total daily dose will be 2 mg.
Day 4
Take a 2 mg strip twice a day. Your total daily dose will be 4 mg.
Day 5
Cut a 2 mg Suboxone strip in 2 pieces. Take one and a half strips (3 mg) twice a day. Your total daily dose will be 6 mg.
Day 6
Take two 2 mg strips (4 mg) twice a day. Your total daily dose will be 8 mg.
Day 7
Take three 2 mg strips (6 mg) twice a day. Your total daily dose will be 12 mg.
If you have additional strips, you may take them to treat any remaining withdrawal that you have. You should be able to decrease other opioids without having significant withdrawal. If you’re still having cravings or using opioids, discuss this with your provider at your follow-up visit and they will decide if your dose needs to be adjusted.
What to do if you have precipitated withdrawal?
You will know that you have this if you start to feel very sick. Severe symptoms may be: aches/pains, vomiting, diarrhea, chills, stomach pains, yawning, runny nose, watery eyes.
For many people with severe withdrawal additional Suboxone will be helpful and you can take a higher dose (8 full strips) at the same time.
If your symptoms do not get better or you’re feeling very sick, you should return to the emergency room.
Other important things to know:
- Keep your Suboxone® in a safe place. Keep away from children and other adults.
- Do not take other medicines or substances that make you sleepy. These may be alcohol or medicines for anxiety (like Xanax® and Klonopin®), sleep or pain.
- Make sure that you have Narcan. You and others you spend time with should know how to use it. If you need more Narcan, ask your provider.
Self-Guided Cross Tapering and Low Dose (8mg) Microinduction Protocol for Outpatients / Patient Discharge
8 mg Buprenorphine Induction
Instructions
Cut an 8 mg strip into 16 pieces. Each piece will be 0.5 mg.
| 0.5 | 0.5 | 0.5 | 0.5 | 0.5 | 0.5 | 0.5 | 0.5 |
| 0.5 | 0.5 | 0.5 | 0.5 | 0.5 | 0.5 | 0.5 | 0.5 |
One 8 mg strip cut into 16 pieces of 0.5 mg each.
Dosing Schedule
| Day | Dose | How often | Pieces at a time |
|---|---|---|---|
| Day 1 | 0.5 mg | Once | 1 piece |
| Day 2 | 0.5 mg | Twice a day | 1 piece |
| Day 3 | 1 mg | Twice a day | 2 pieces |
| Day 4 | 2 mg | Twice a day | 4 pieces |
| Day 5 | 3 mg | Twice a day | 6 pieces |
| Day 6 | 4 mg | Twice a day | 8 pieces |
| Day 7 | 6 mg | Twice a day | 12 pieces |
| Day 8 | 8 mg | Twice a day | 1 whole strip |
Cross Tapering and Low Dose Microinduction Protocol for Admitted Patients Using Methadone
Rapid Low Dose Buprenorphine Initiation in a Detox Setting
Cross-Tapering with Methadone and Buprenorphine
Background
Buprenorphine is a mu opioid receptor partial agonist that is indicated for pain management and the treatment of opioid use disorder (OUD). Traditional induction for patients with OUD requires a patient to experience opioid withdrawal (measured via COWS scores) prior to buprenorphine initiation. This is necessary in order to prevent the experience of precipitated withdrawal due to the partial agonist effects displacing the full opioid agonist when using traditional (4-8mg) doses of buprenorphine. Micro-dosing of buprenorphine uses the buprenorphine buccal films (Belbuca®), which are dosed in micrograms, allowing for the induction of buprenorphine without the need to first experience withdrawal or the risk of precipitated withdrawal since the lower doses do not displace the full agonist opioid with the same intensity as the 10-20x higher doses usually initiated.
When starting with the lower dose approach in the detox setting, dosing can be repeated q 2-6 hours and can be gradually increased over 3-4 days to achieve full maintenance dosing while maintaining the methadone at 30mg. Case reports and case series support this approach in hospital as well as outpatient settings, and we have successfully completed buprenorphine induction using this approach in several patients in our health system, and it is supported by published literature (see references at end).
Intent
For use as an alternative to standard or higher-dose buprenorphine induction strategies in patients admitted for detoxification (“detox”) or medically managed withdrawal, in order to bridge patients safely to buprenorphine during a rapid inpatient admission with the goal of discharging on MOUD (buprenorphine).
The literature supports the use of MOUD (buprenorphine) rather than an abstinence-based treatment with methadone tapering to no medications at discharge.
Intended Patient Population: Detox or Rehab Setting
- Patients requesting buprenorphine treatment for OUD who have had a history of opioid use (fentanyl) disorder
AND
Who wish to avoid the need for moderate withdrawal symptoms prior to induction with higher doses of buprenorphine.
- For example, any or all of the below conditions:
- Patients wishing to transition from methadone to buprenorphine
- Patients with chronic, heavy use of either intravenous or intranasal fentanyl
- Patients who have experienced prior precipitated withdrawal
- For example, any or all of the below conditions:
Procedure: Microdosing Regimen Using Belbuca® and Suboxone® (Buprenorphine/naloxone)
- Day 1: 150 mcg buccal film q3h (can be given in the absence of withdrawal symptoms). Methadone 30mg initial dose.
- Day 2: 450 mcg buccal film q6h x 2 doses, followed by 900 mcg Belbuca® (2 x 450 mcg) q6h x 2 doses. Methadone 30mg.
- Day 3: Buprenorphine/naloxone 2 mg SL q6h. Methadone 30mg.
- Day 4: Discharge Rx buprenorphine 8mg BID or TID (16-24mg), no full agonist.
| Day | Total Daily Dose | Dosing | How to Take | Methadone or Full Agonist |
|---|---|---|---|---|
| 1 | 1200 mcg | 150 mcg Belbuca® q3h | 1 film q3h x 8 doses | Full dose |
| 2 | 2700 mcg | 450 mcg Belbuca® q6h x 2 doses, then 900 mcg (2 x 450 mcg) q6h x 2 doses | 1 film q6h x 2 2 films q6h x 2 |
Full dose |
| 3 | 8 mg | 2 mg q6h x 4 doses | 1 film q6h | Full dose |
| 4 | Rx 16 or 24 mg | 8 mg BID or TID | 1 8mg film BID or TID | Discontinue |
Other Considerations: Use Comfort Medications Aggressively
- Acetaminophen, ibuprofen, or other NSAIDs for aches/pains
- Ibuprofen 600 mg q6h, MDD 2400 mg, max 7 days
- Acetaminophen 1000 mg PO q6h
- Clonidine for withdrawal symptoms
- 0.1-0.2 mg q4h
- Hold if dizzy or systolic BP < 100; taper if given for >7 days
- Hydroxyzine for anxiety and withdrawal symptoms
- 50-100 mg 4x daily (MDD 200 mg/day)
- Dicyclomine for abdominal cramping
- 10 mg PO q6h PRN
- Trazodone for insomnia and depressive symptoms
- 50-200 mg 1 hour before sleep, MDD 200 mg
- Consider benzodiazepines; can use clonazepam
- 0.5 mg BID
- Loperamide
- 2-4 mg q2h PRN diarrhea
Discharge Considerations
- Provide Narcan on discharge, preferably filled and handed to patient prior to leaving.
- Close outpatient follow-up.
References
- Antoine D, Huhn AS, Strain EC, Turner G, Jardot J, et al. Method for successfully inducting individuals who use illicit fentanyl onto buprenorphine/naloxone. Am J Addict. 2020.
- Brar R, Fairbairn N, Sutherland C, Nolan S. Use of a novel prescribing approach for the treatment of opioid use disorder: Buprenorphine/naloxone micro-dosing – a case series. Drug Alcohol Rev 2020;39:588-594.
- Klaire S, Zivanovic R, Barbic SP, Sandhu R, Mathew N, Asar P. Rapid micro-induction of buprenorphine/naloxone for opioid use disorder in an inpatient setting: A case series. Am J Addict 2019;28:262-265.
- Rozylo J, Mitchell K, Nikoo M, Durante SE, Barbic SP, et al. Case report: Successful induction of buprenorphine/naloxone using microdosing schedule and assertive outreach. Addict Sci Clin Pract. 2020;15:2. https://doi.org/10.1186/s13722-020-0177-x
- Weimer MB, Guerra M, Morrow G, Adams K. Hospital-based Buprenorphine Micro-dose Initiation. J Addict Med. 2020. doi:10.1097/ADM.0000000000000745
